AI malnutrition detection in EHRs boosts hospital ROI 5-20×
Healthleap’s language-model platform scans EHR notes to surface undiagnosed malnutrition, cutting stays and boosting reimbursements—see the financial upside.
Key takeaways
- Deploying AI that extracts clinical concepts from unstructured notes can identify up to 50% of hidden malnutrition cases, directly reducing length of stay.
- Partner contracts priced by licensed bed count and tied to hard ROI (5×-20×) provide a clear financial justification for C-suite approval.
- Scaling the model to additional conditions requires incremental engineering spend but leverages the same EHR integration pipeline, minimizing new implementation risk.
AI-driven risk scoring
Healthleap’s AI platform turns every adult inpatient’s chart into a nightly risk-score, surfacing hidden conditions such as malnutrition and delirium that often escape early detection. By pulling both structured fields — labs, vitals, weights — and unstructured clinician notes, the system generates a composite score that is written into the care team’s existing workflow each morning. The thesis is simple: a scalable, language-model-driven review of existing data can uncover up to half of inpatient malnutrition cases and generate a measurable financial return.
Clinical and financial impact
The platform is already deployed in more than 50 hospitals, including Penn Medicine, Cedars-Sinai, Intermountain, Houston Methodist and Emory Healthcare. In its pilot at the Hospital of the University of Pennsylvania, the malnutrition program produced $23.8 million in annualized financial impact, split between $6.3 million from additional reimbursement and $17.5 million from shorter stays. Across its customer base, Healthleap reports that every client has achieved a “hard ROI” of at least 5×, with some seeing over 20× annual total ROI. Those figures stem from two levers: accelerated discharge (reducing bed-day costs) and capture of higher-value DRG reimbursements once malnutrition is documented and treated.
Business model and contract structure
The business model reinforces the ROI narrative. Contracts run three years and are priced according to a hospital’s licensed bed count, but a portion is outcome-based. Healthleap ties payment to the hard ROI validated by the hospital finance team, guaranteeing multiples of the contract price. This structure shifts financial risk to the vendor while giving executives a clear metric for board reporting.
Implementation and expansion roadmap
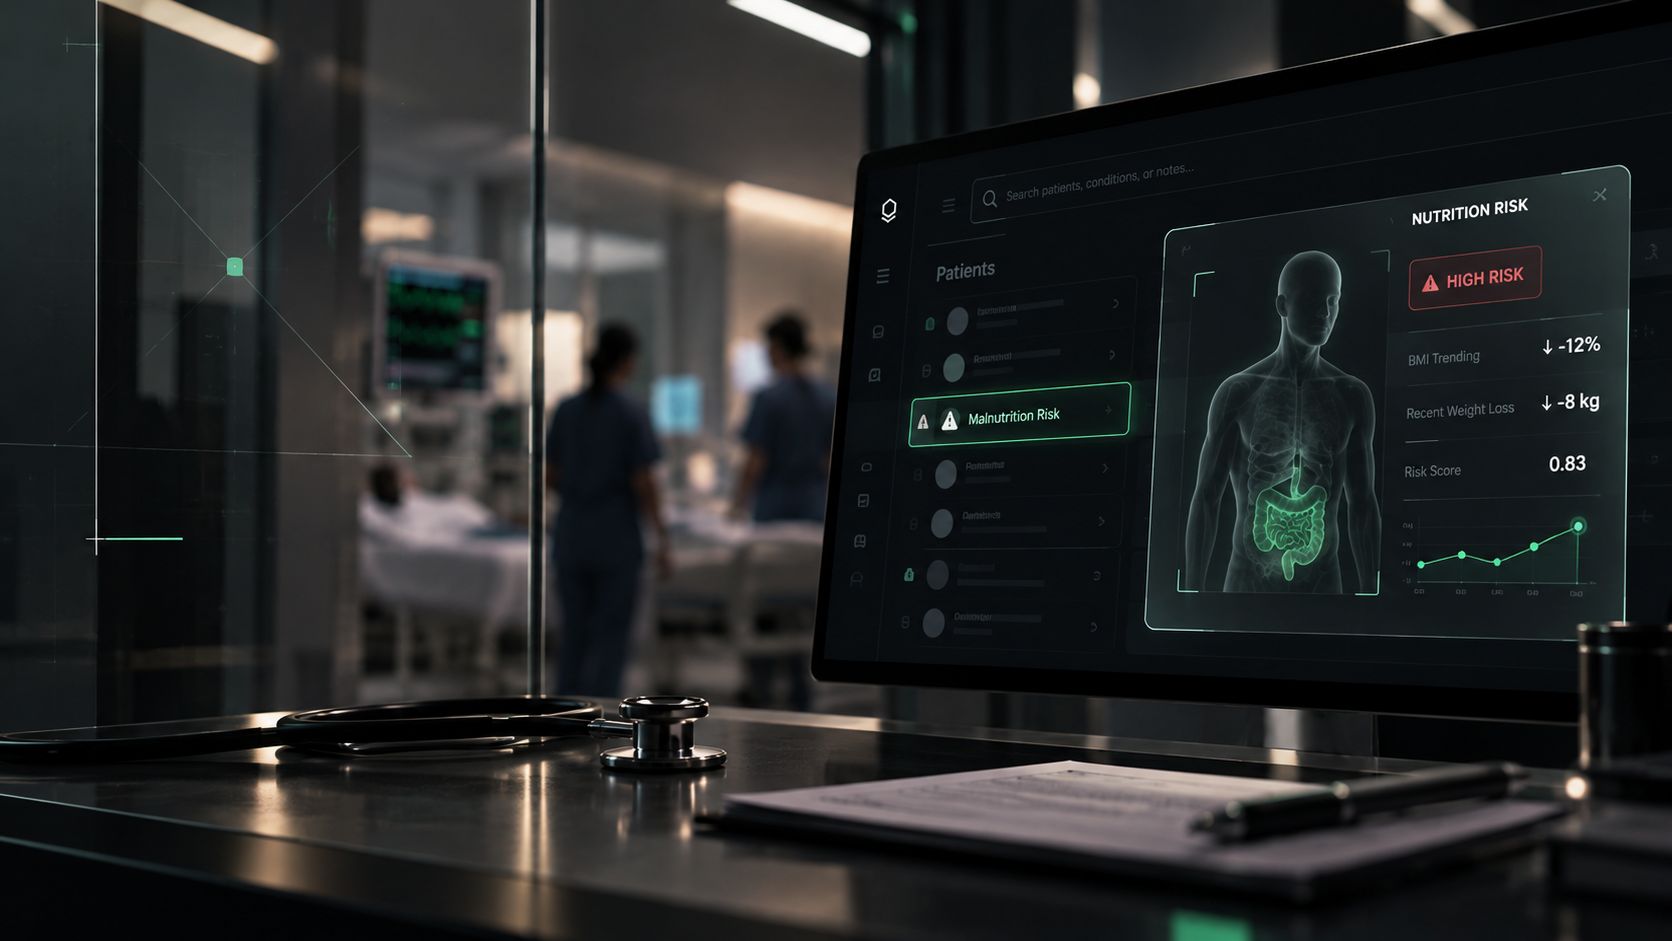
From an operational standpoint, the core integration is a single plug-in to the hospital’s electronic health record (EHR). Each night the system ingests the full record—labs, vitals, medication orders, diet orders, diagnoses, and free-text notes—then runs language-model extractions for affirmative or negated mentions of key clinical concepts (e.g., “poor appetite,” “weight loss,” “muscle wasting”). The extracted signals feed a risk model calibrated on historical outcomes; the resulting score appears in a dashboard that sits within the team’s usual order-entry or patient-list view. Because the platform uses existing EHR data, there is no need for additional data entry or separate screening workflows, keeping staff burden low.
Healthleap’s roadmap leverages the same pipeline to add 40+ conditions, spanning aspiration pneumonia, pressure ulcers, and readmission risk for congestive heart failure. Each new condition adds a layer of concept extraction and a calibrated risk model but reuses the nightly ingest, the EHR plug-in, and the dashboard delivery mechanism. The company plans to allocate its fresh $38 million funding to engineering, product, sales and customer success to accelerate this breadth-first expansion.
For hospital leaders, the immediate decision point is whether to adopt an AI-driven screening layer that can be embedded into current workflows without new staffing. The potential upside—shorter stays, higher reimbursements, and a quantifiable ROI—must be weighed against the upfront integration effort and the need to validate the specific risk models for each condition in their patient population.
To act, executives should:
- Pilot the malnutrition module in a defined unit – low-risk, high-volume wards provide quick data on length-of-stay reduction; downside is that results may not generalize to specialty units.
- Negotiate an outcome-based contract – lock in a 5× ROI clause to protect the budget; the trade-off is a potentially higher per-bed price if the model underperforms.
- Map the integration pathway with the EHR vendor – ensure nightly data feeds can be scheduled without disrupting existing interfaces; the risk is added IT coordination time.
- Plan for condition expansion – allocate resources for clinical validation of new risk models once the initial module proves ROI; early expansion carries validation cost but accelerates broader cost savings.
Each morning, we write a risk score into the care team’s existing workflow with a dashboard accessible that holds additional information about the patients’ trends.

Amazon drops NDAs with governments, aims to quell data-center backlash
AWS chief says ending nondisclosure deals and $1 bn community spending will restore trust as moratoriums rise across the U.S.

FDA’s READI-Home pilot launches with first five participants
The FDA’s READI-Home program begins, letting five early adopters test home-based diagnostic tools under a new regulatory framework – here’s what leaders must do now.
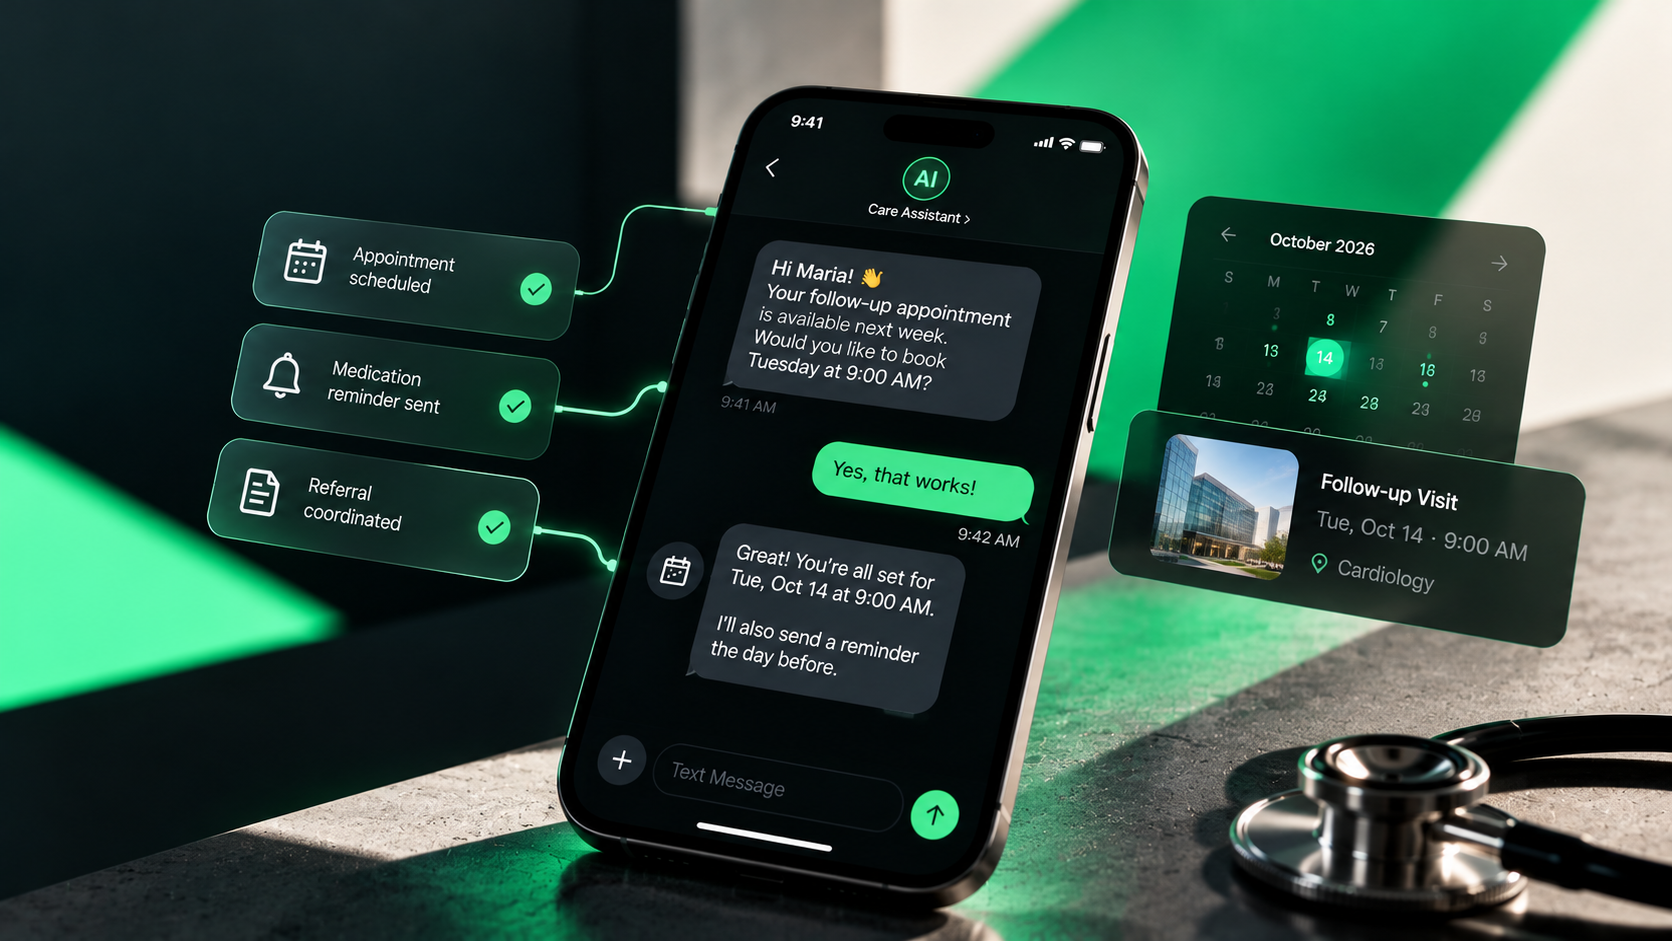
AI agents in text messages: a new channel for patient coordination
Messaging-based AI assistants let clinicians automate scheduling, reminders and referrals without extra apps, reshaping how hospitals streamline patient touchpoints.